Medical benefit, not vision plan.
FDA-approved cross-linking for documented progressive keratoconus is generally a medical claim. We check the right policy before quoting anything.
Cross-linking usually runs through medical insurance, not the vision plan your employer talks about at open enrollment. We verify what applies to your policy and put the numbers in writing before anything is scheduled.
Around Las Colinas, most people have a solid employer benefits package and a vision plan they think of as their eye insurance. Keratoconus does not follow that intuition. Progressive keratoconus is a medical diagnosis, and FDA-approved cross-linking is generally handled as a medical benefit — which means the vision plan that covers the annual exam and a frame allowance is often not the policy that matters here.
That single distinction accounts for most of the confusion we hear, and it usually comes up after a patient has already been quoted a number by someone reading the wrong card. Our team verifies which of your benefits applies, what your plan requires as evidence of progression, and what the out-of-pocket portion would actually be — in writing, before anything is scheduled.
Clinically the pathway is unchanged: cross-linking to halt progression, CTAK to reshape a cornea already distorted by the cone, specialty lenses to refine what remains. Dr. Shehz is a cornea-trained surgeon performing cross-linking and CTAK at our Plano facility, about thirty minutes from Irving on the PGBT or 635.
Progressive keratoconus is a medical diagnosis. The vision plan covering your annual exam is usually not the policy in play.
FDA-approved cross-linking for documented progressive keratoconus is generally a medical claim. We check the right policy before quoting anything.
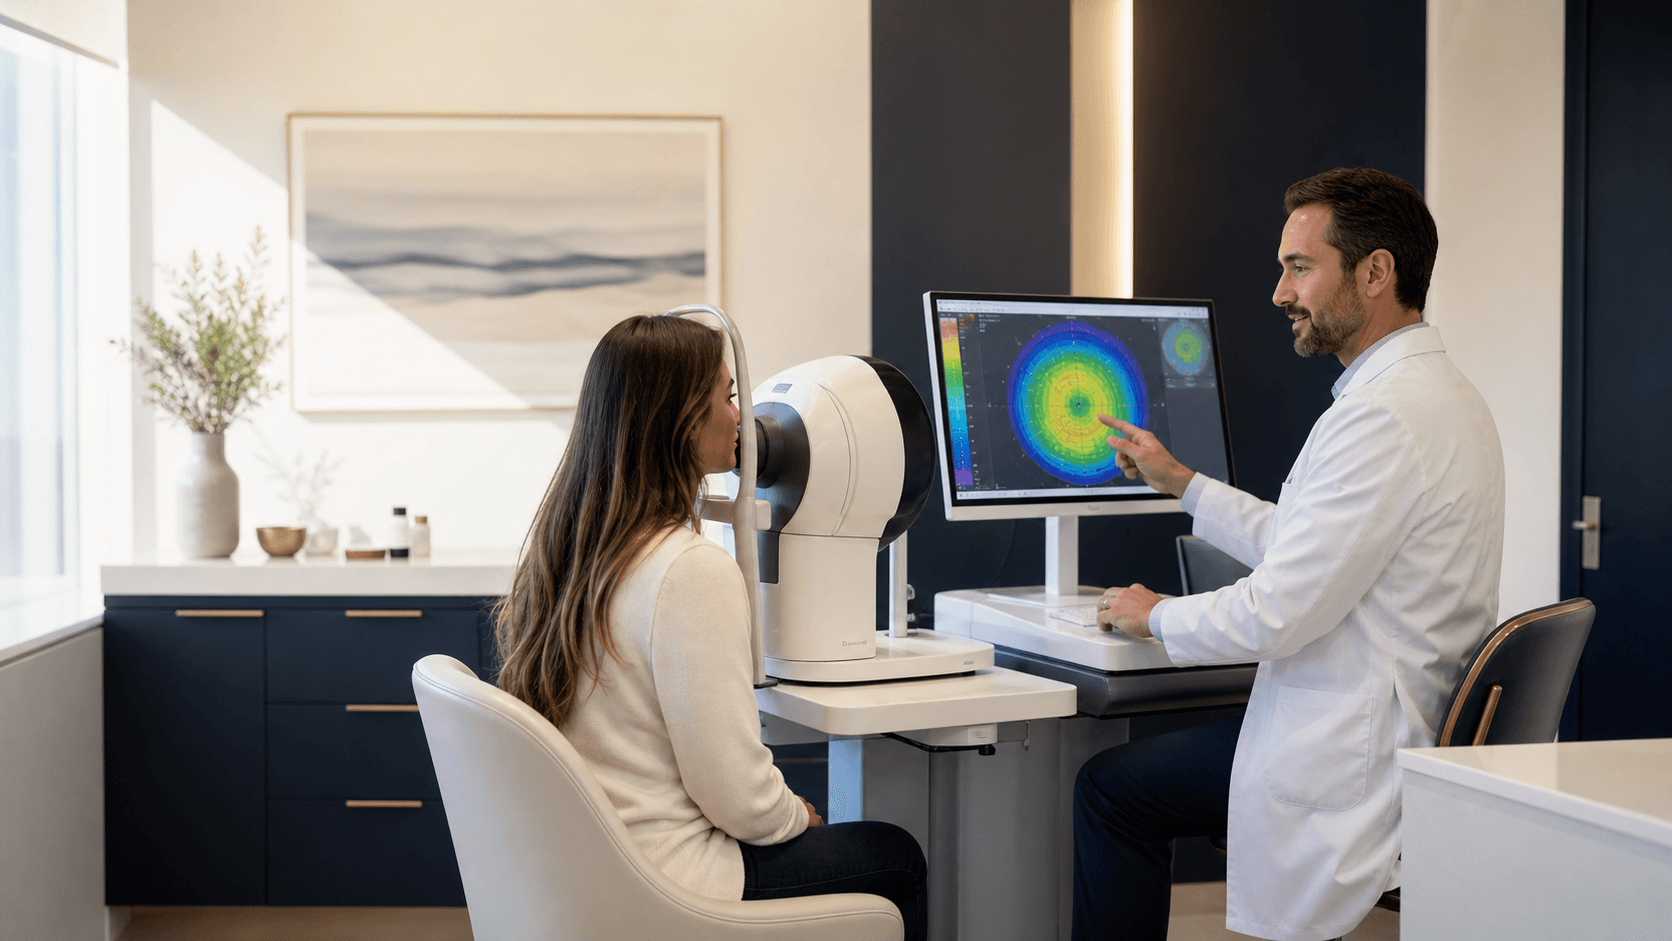
Plans want evidence the cornea is changing. Topography and pachymetry produce exactly that record, which is one reason the mapping matters twice over.
You get the verified benefit and the out-of-pocket portion in writing ahead of scheduling. No surgery-day surprises.
A cone-shaped cornea is progressive, it is irregular, and it is hard to correct. Those are three different problems. Cross-linking answers the first by halting progression. It does not answer the second — a stabilized cornea is still a distorted one.
CTAK answers the second. By adding laser-shaped donor tissue inside your own cornea, it works toward a more regular surface, which is what makes the third problem tractable: glasses and contacts start working again. Which combination your eye needs, and in what order, is what the consultation is for.
Which of these your eye needs, and in what sequence, comes out of the corneal maps rather than off a menu. Cross-linking is the time-sensitive one. Reshaping can wait for a stable cornea, and usually should.

A piece of sterilized donor cornea, laser-shaped to the map of your own eye and placed inside your cornea to round the cone back toward its natural shape. Nothing is removed, so a transplant stays on the table rather than behind you.

The FDA-approved treatment that uses riboflavin and ultraviolet light to strengthen the collagen bonds holding your cornea's shape. It does not reverse keratoconus — it stops it getting worse, which is why timing matters more here than anywhere else.

Scleral and rigid gas-permeable lenses vault over an irregular cornea and give light a smooth surface to pass through. Often the bridge between diagnosis and stability — and, after CTAK, frequently easier to fit and wear.
Keratoconus care is a sequence, and the order is not arbitrary. Stabilizing a cornea that is still changing comes first, because reshaping one that has not settled does not hold. Each step below answers a different question about your eye.

Corneal cross-linking strengthens the collagen bonds holding your cornea's shape. It is the time-sensitive step: it protects the cornea you still have rather than recovering the cornea you had.

CTAK places a laser-shaped piece of sterilized donor tissue inside your own cornea, working the cone back toward a regular shape. Nothing of yours is removed, which is what separates it from a transplant.

Once the cornea is stable and more regular, glasses or specialty lenses do the remaining work — and a more regular cornea is markedly easier to fit and more comfortable to wear against.
North on the President George Bush Turnpike, or 635 to 75 — about thirty minutes from Irving. Ground floor with free parking.
8080 Independence Pkwy, Suite 155
Plano, TX 75025
A keratoconus consultation takes about 60–90 minutes with full corneal mapping. Bring your medical insurance card as well as any vision plan card — the first is usually the one that matters.
Open Monday–Friday 8:00–5:00 and Saturday 9:00–3:00, with English- and Spanish-speaking staff. Questions before booking? Call 214-972-2020 and a human answers.
Don't see your question? Call 214-972-2020 or book a visit and ask Dr. Shehz directly.
Talk to our team, no pressure, no sales pitch. We answer the question, not the upsell.
What your cornea needs is a question for the maps. What it costs you is a question for your policy. You should have both answers before you decide anything, and you should have the second one in writing.
Cost, safety, candidacy — the questions patients actually ask, answered in plain English in our patient education library.
A protocol-specific CXL recovery guide for Plano keratoconus patients, including epi-off and epi-on differences, vision changes, follow-up, and warning signs.
Read articleLearn how serial corneal maps, thickness, age, documented progression, specialty lenses, and treatment protocol determine when CXL should be considered.
Read articleLearn when CTAK donor-tissue reshaping may be considered for selected stable keratoconus and how it differs from CXL, specialty lenses, and corneal transplant.
Read articleCXL cost and coverage depend on keratoconus progression, corneal maps, insurance authorization, deductible status, treatment protocol, and the written estimate.
Read articleLearn how corneal thickness and tomography affect LASIK candidacy and when PRK, EVO ICL, SMILE, CXL-first care, or monitoring may be safer.
Read articleA LASIK rejection does not end the discussion. Learn how the reason - corneal shape, thickness, prescription, dry eye, or age - guides safer alternatives.
Read articleExplore how dry-eye symptoms, tear-film stability, and corneal health affect PRK candidacy, with practical testing questions for Dallas-Fort Worth patients.
Read articleCorneal mapping, a progression assessment, and a verified benefits check in writing. About thirty minutes from Irving on the PGBT. Call 214-972-2020 or book online.