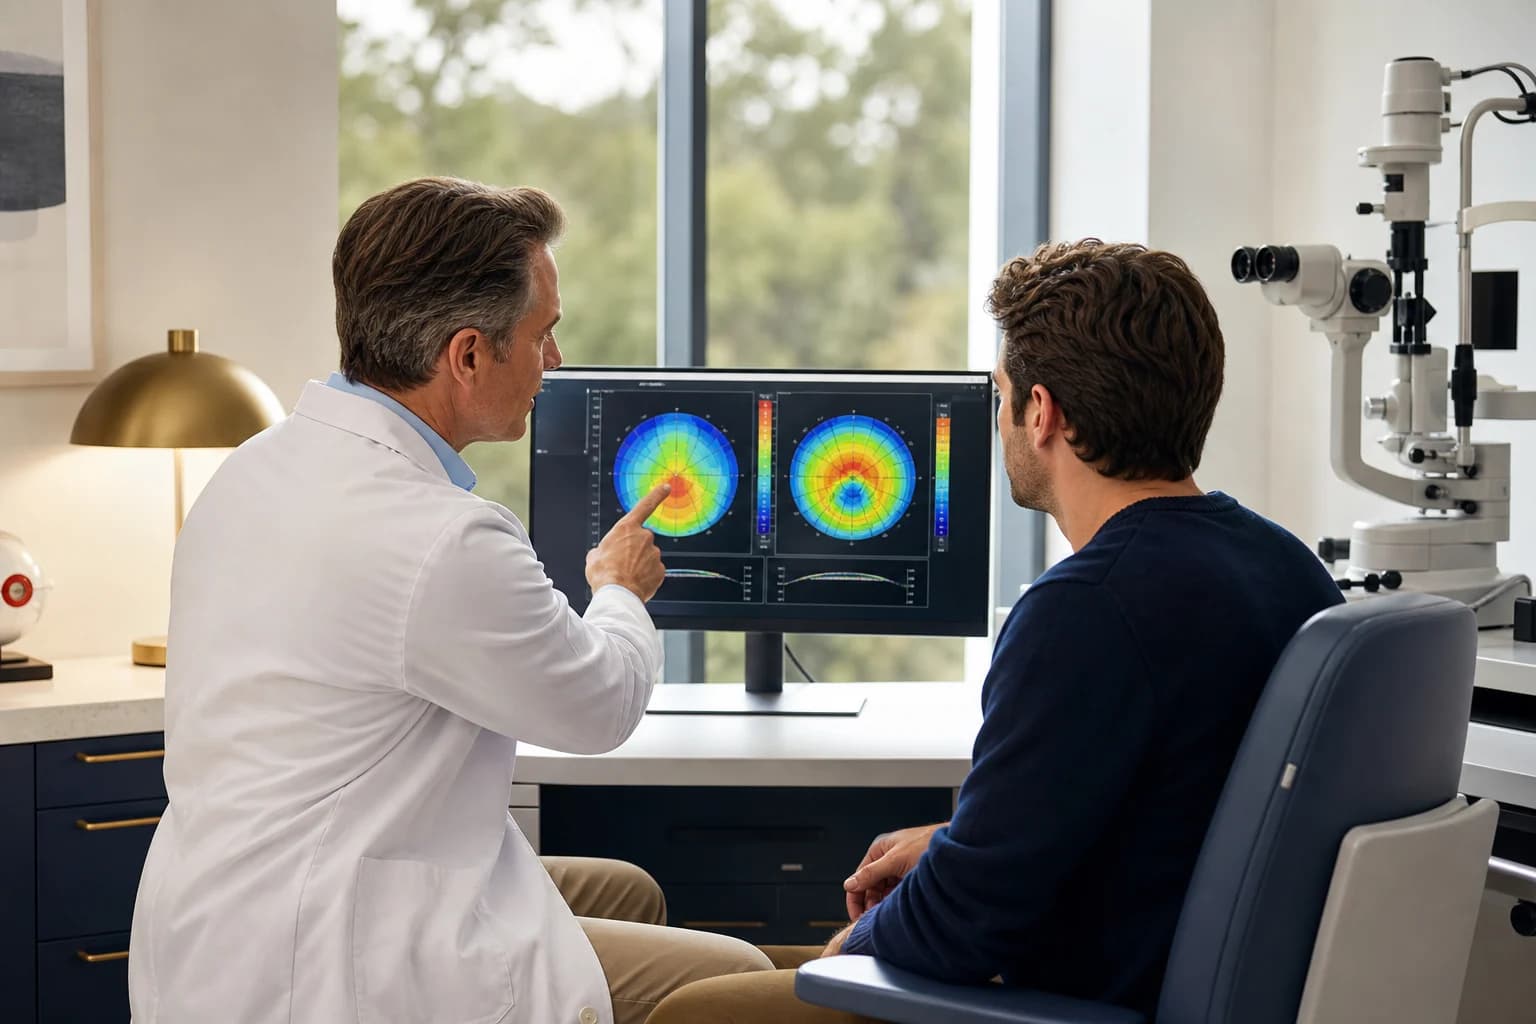
Dry eyes do not lead to a simple yes-or-no answer about PRK. The cause and control of the surface problem, the reliability of measurements, and the health of the cornea all matter. Treating dry eye before deciding on surgery may be the most useful next step.
The PRK eye surgery page explains the procedure itself. This guide addresses the narrower question of ocular-surface readiness; it does not assume that thin corneas or contact-lens discomfort make PRK the right choice.
Why does the ocular surface matter before PRK?
PRK reshapes corneal tissue after the surface epithelium is removed. The surface then needs to heal. Existing dryness, inflammation, or unstable vision deserves attention before treatment rather than being dismissed as something that surgery will solve.
The AAO overview of PRK describes the examination and healing considerations involved in surface treatment. A flapless operation is still an operation on the cornea. Being unsuitable for LASIK does not by itself make a person suitable for PRK.
Explain how the symptoms behave: whether they occur only with contacts, build up during the day, or persist even without lenses. That distinction helps frame the evaluation, although symptoms alone cannot identify the cause.
What should a dry-eye assessment establish?
Ask whether the problem involves tear production, evaporation, eyelid inflammation, or a combination. The clinician may assess the tear film, eyelid glands, surface staining, and other findings based on the presentation. Not every patient needs the same set of tests.
It is useful to bring the names of drops and treatments you have tried, how often you use them, and whether they helped. Include medications, prior eye surgery, and relevant medical history. Do not stop a prescribed medication simply because it appears on an online list of possible dry-eye contributors.
Our dry-eye evaluation page explains the cause-based approach. The objective before PRK is not just feeling better for a few hours; it is understanding whether the surface and measurements are sufficiently stable for planning.
What would make postponing the decision sensible?
Persistent symptoms, significant surface findings, or inconsistent measurements may lead the clinician to treat the ocular surface and reassess. Ask what finding needs to improve, when it will be rechecked, and whether the treatment plan changes the timing of surgery.
For someone arranging leave from a job in Richardson or Carrollton, this is a reason to confirm the testing sequence before committing to a surgery date. Keep the first evaluation and final treatment planning separate until the team says the measurements are ready.
Request contact-lens instructions before traveling to Plano. The contact-lens preparation guide explains why lens type and measurement stability can affect the timetable.
How is a thin cornea different from a dry eye?
Thickness and tear-film health are different issues. An eye can have one, both, or neither. A healthy but relatively thin cornea still needs a tissue-budget assessment; an irregular or suspicious map may raise a different concern that requires further investigation.
Avoid treating "thin cornea" as a shortcut to PRK, or assuming surface laser treatment makes an abnormal map safe. Ask which finding is limiting the options and whether there is evidence of keratoconus or another corneal condition.
The PRK versus EVO ICL guide addresses the broader comparison. EVO ICL avoids removing corneal tissue, but is intraocular surgery with its own anatomical requirements and risks. It does not cure dry-eye disease.
Which aftercare questions belong in the decision?
If PRK remains an option, discuss the drop plan, early visits, and who to contact if symptoms change. Do not assume your preoperative dry-eye routine will remain unchanged after surgery. Ask the clinician which products to continue and how they fit with postoperative prescriptions.
For the overall calendar, use the PRK recovery guide. For the specific issue of haze and outdoor protection, read PRK haze and sun protection. Keeping these questions separate helps you prepare without treating every postoperative symptom as dry eye.
Severe pain, increasing redness, discharge, or sudden worsening of vision after treatment needs prompt assessment. Those changes should not be managed by adding more lubricating drops and waiting.
What should DFW patients bring to the consultation?
Bring current glasses, contact-lens details, prior prescriptions, relevant test reports, and a brief symptom history. Note tasks that are difficult, such as long monitor sessions or driving with air conditioning blowing toward the face. These observations are conversation starters, not a diagnosis.
Visionary Eye Surgery is in Plano. Patients from Allen and other DFW communities should confirm whether repeat testing may be required and who will coordinate existing dry-eye care. Contact the practice to check preparation instructions. A useful outcome is a clear plan to treat, retest, proceed, or wait, with the reason explained.
Keep Reading
Your exam can clarify which options fit your eyes. Visit our Plano team from anywhere in DFW.
Book a free visit