Cornea-trained surgeon.
Dr. Shehz has specific training in corneal procedures including CXL, CTAK, and keratoconus management. Not every ophthalmologist performs cross-linking, and fewer offer tissue addition.
Cross-linking halts keratoconus. It does not undo the cone already there — which is why a stabilized cornea can still refuse to correct. CTAK addresses the shape itself, and both are performed 15 minutes south in Plano.
A keratoconus diagnosis arrives with one urgent question: who in DFW has the corneal expertise to evaluate it, plan the treatment, and carry it out? It is the same question whether you are a student whose prescription keeps moving, a professional who cannot get contacts to sit right, or a parent whose teenager was just flagged at a routine exam.
The first answer is cross-linking. Riboflavin and ultraviolet light strengthen the collagen bonds in a weakening cornea and halt the cone-shaped distortion keratoconus causes. It is time-sensitive in the most literal way: it protects the cornea you still have rather than recovering the cornea you had, so the months after a diagnosis genuinely count.
What gets said less often is that halting progression is not the same as restoring vision. A stabilized cornea is still a distorted one, and plenty of patients finish cross-linking only to find that glasses and contacts still will not sharpen. CTAK is the second answer — sterilized donor tissue, laser-shaped to your own corneal map and placed inside your cornea to round the cone back toward a regular shape, with none of your own tissue removed.
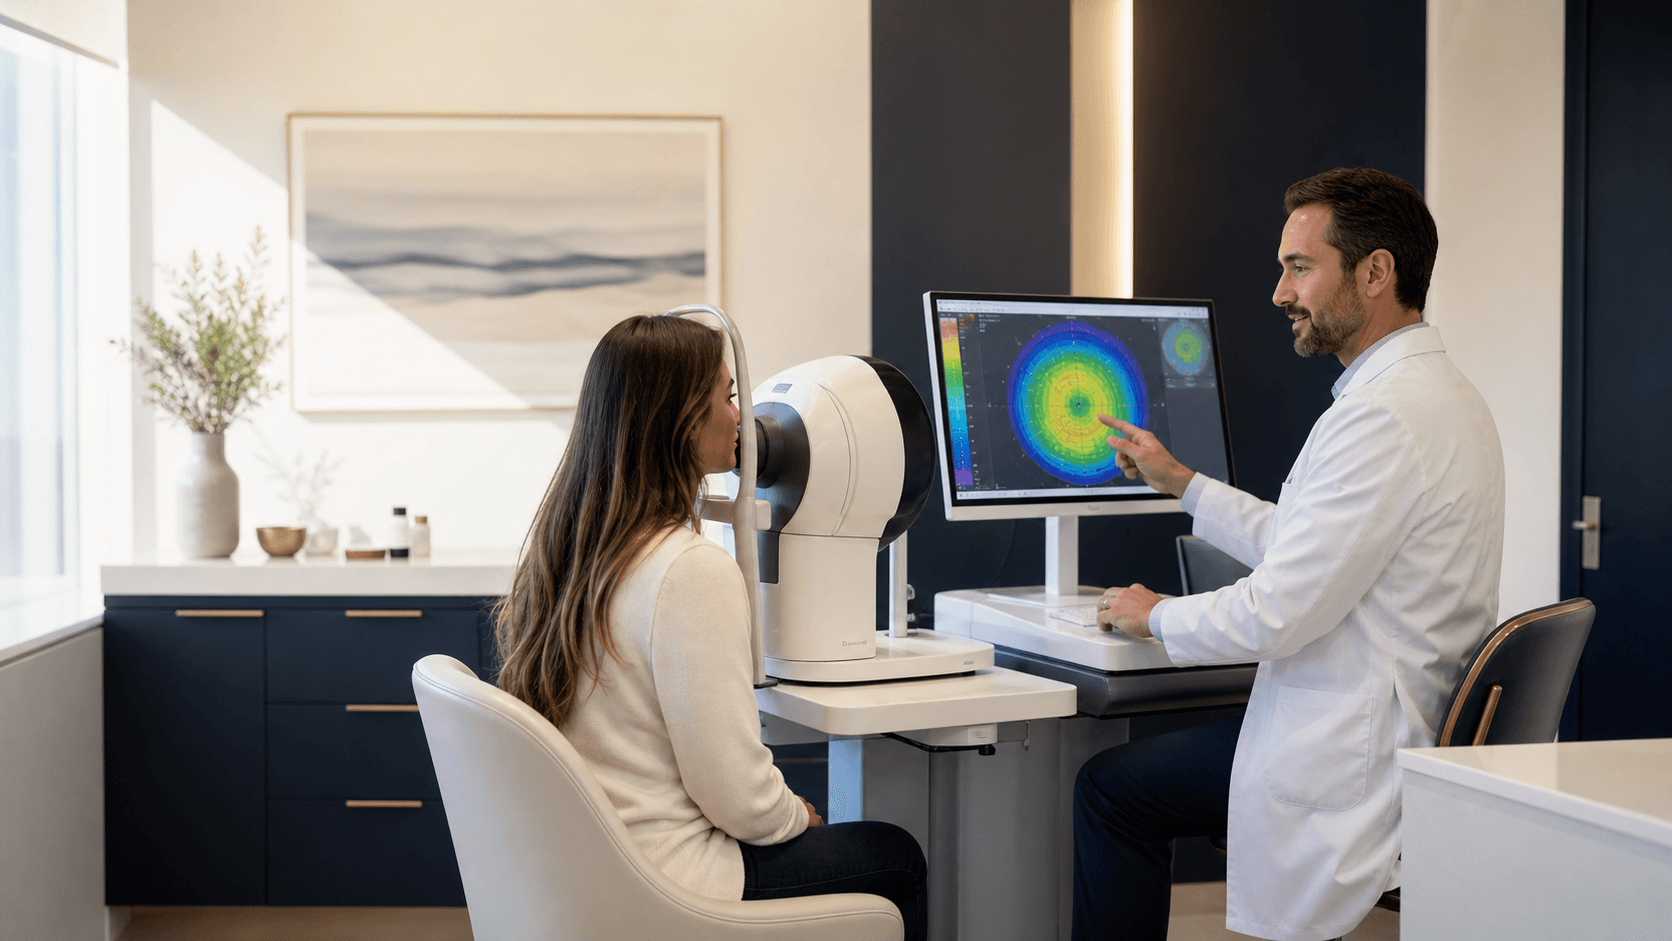
Dr. Shehz is a cornea-trained surgeon performing both at our Plano facility, about 15 minutes from Frisco on the Dallas North Tollway or the Sam Rayburn. Consultations include corneal topography, pachymetry, and a progression assessment — the diagnostics that decide whether to treat now or monitor. We accept referrals from Frisco optometrists directly and send reports back.
Cross-linking protects the cornea you still have. CTAK works on the shape it has already taken. Most plans need to account for both.
Dr. Shehz has specific training in corneal procedures including CXL, CTAK, and keratoconus management. Not every ophthalmologist performs cross-linking, and fewer offer tissue addition.
Corneal topography, pachymetry, and progression assessment determine whether treatment is needed now — not every keratoconus case requires immediate intervention, and we will say so.
Moving from cross-linking to CTAK is a clinical decision here, not a referral and a three-month gap. Specialty lens fitting sits with the same team.
A cone-shaped cornea is progressive, it is irregular, and it is hard to correct. Those are three different problems. Cross-linking answers the first by halting progression. It does not answer the second — a stabilized cornea is still a distorted one.
CTAK answers the second. By adding laser-shaped donor tissue inside your own cornea, it works toward a more regular surface, which is what makes the third problem tractable: glasses and contacts start working again. Which combination your eye needs, and in what order, is what the consultation is for.
Which of these your eye needs, and in what sequence, comes out of the corneal maps rather than off a menu. Cross-linking is the time-sensitive one. Reshaping can wait for a stable cornea, and usually should.

A piece of sterilized donor cornea, laser-shaped to the map of your own eye and placed inside your cornea to round the cone back toward its natural shape. Nothing is removed, so a transplant stays on the table rather than behind you.

The FDA-approved treatment that uses riboflavin and ultraviolet light to strengthen the collagen bonds holding your cornea's shape. It does not reverse keratoconus — it stops it getting worse, which is why timing matters more here than anywhere else.

Scleral and rigid gas-permeable lenses vault over an irregular cornea and give light a smooth surface to pass through. Often the bridge between diagnosis and stability — and, after CTAK, frequently easier to fit and wear.
Keratoconus care is a sequence, and the order is not arbitrary. Stabilizing a cornea that is still changing comes first, because reshaping one that has not settled does not hold. Each step below answers a different question about your eye.

Corneal cross-linking strengthens the collagen bonds holding your cornea's shape. It is the time-sensitive step: it protects the cornea you still have rather than recovering the cornea you had.

CTAK places a laser-shaped piece of sterilized donor tissue inside your own cornea, working the cone back toward a regular shape. Nothing of yours is removed, which is what separates it from a transplant.

Once the cornea is stable and more regular, glasses or specialty lenses do the remaining work — and a more regular cornea is markedly easier to fit and more comfortable to wear against.
Dallas North Tollway or Sam Rayburn south — about 15 minutes from Frisco. Ground floor with free parking.
8080 Independence Pkwy, Suite 155
Plano, TX 75025
A cornea consultation includes topographic mapping and takes about 60–90 minutes. CXL itself is an outpatient procedure performed at our Plano facility.
Open Monday–Friday 8:00–5:00 and Saturday 9:00–3:00, with English- and Spanish-speaking staff. Questions before booking? Call 214-972-2020 and a human answers.
Don't see your question? Call 214-972-2020 or book a visit and ask Dr. Shehz directly.
Talk to our team, no pressure, no sales pitch. We answer the question, not the upsell.
Cross-linking answers whether keratoconus keeps getting worse. It does not answer whether your cornea is regular enough to correct. If the first is settled and the second is not, CTAK is the part of the pathway still open.
Explore cost, recovery, and candidacy at your own pace.
A protocol-specific CXL recovery guide for Plano keratoconus patients, including epi-off and epi-on differences, vision changes, follow-up, and warning signs.
Read articleLearn how serial corneal maps, thickness, age, documented progression, specialty lenses, and treatment protocol determine when CXL should be considered.
Read articleLearn when CTAK donor-tissue reshaping may be considered for selected stable keratoconus and how it differs from CXL, specialty lenses, and corneal transplant.
Read articleA cornea consultation determines whether cross-linking is the right step, whether reshaping is warranted, and how much vision can be preserved. About 15 minutes from Frisco. Call 214-972-2020 or book online.