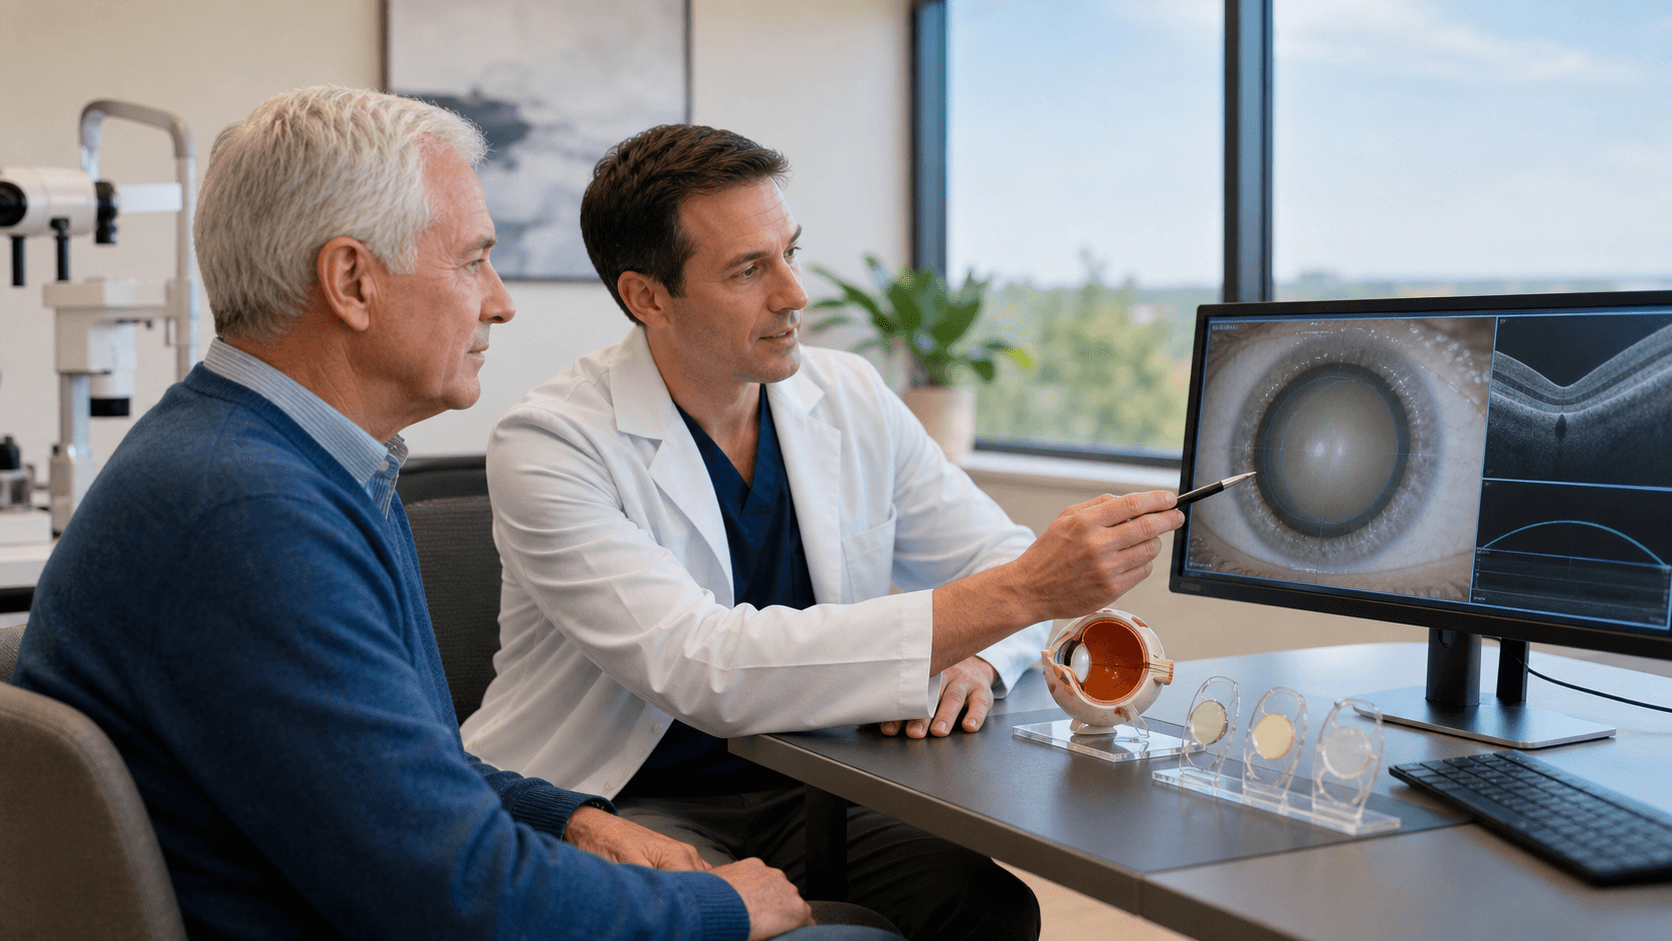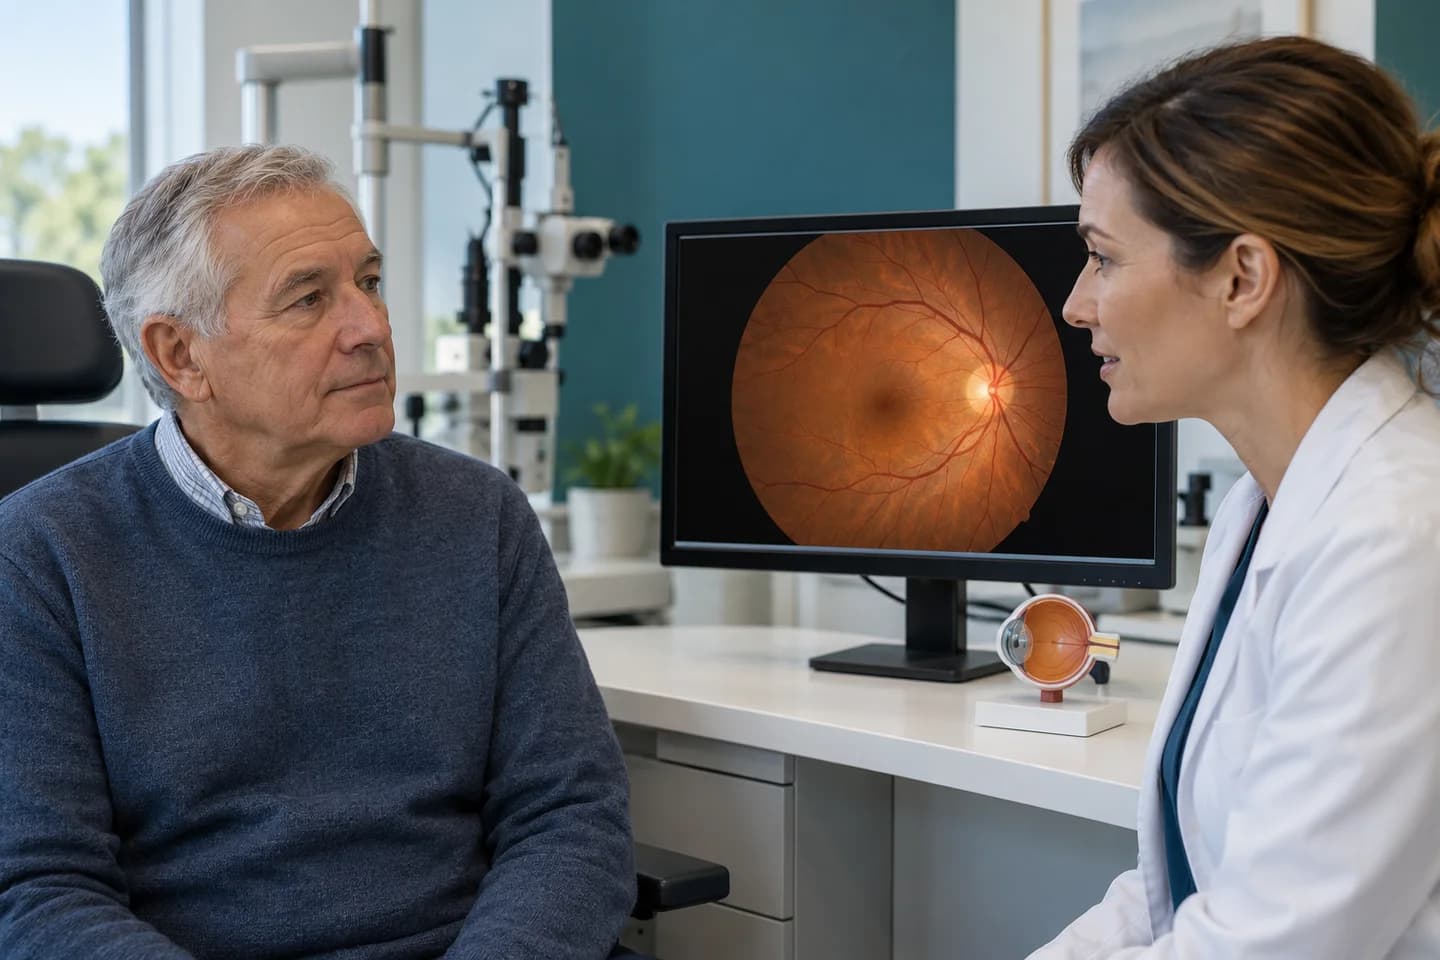
Diabetes does not automatically prevent cataract surgery, but the plan needs to account for the retina as well as the cloudy lens. Diabetic retinopathy or macular swelling can affect timing, lens discussions, and the amount of improvement expected. Removing a cataract does not treat every diabetic eye problem.
The cataract procedure page explains surgery generally. This guide is for the additional questions to ask when diabetes is part of your medical history.
Why does the retina matter before lens surgery?
A cataract affects the natural lens at the front of the eye. Diabetic retinal disease affects light-sensitive tissue at the back. Both can contribute to blurred vision, and a new lens cannot by itself repair damage in the retina.
Ask the examiner to explain which finding is limiting vision and whether the view of the retina is adequate. Depending on the findings, additional imaging or a retina opinion may be needed. A careful discussion separates what surgery may improve from what still needs separate care.
Does diabetic retinopathy change the timing?
It can. Active retinal disease or macular edema may require coordination before or around cataract surgery. The appropriate sequence depends on your examination and the clinicians managing the conditions, not a universal timetable.
Ask who will coordinate the plan and whether your retina clinician needs to review the proposed date. Avoid assuming that a delay means surgery is impossible or that an early opening means it should proceed immediately. The reason for the timing should be clear to you and the other clinicians involved.
Does diabetes determine the implant choice?
Not by itself. The health of the macula and optic nerve, your visual priorities, and the trade-offs of the proposed lens all matter. Ask how current findings affect the expected benefit of a particular implant rather than selecting from a price list.
The cataract lens comparison covers broader choices. At the visit, ask for a recommendation tied to your test results. A premium option is not a substitute for assessing the retina or setting realistic expectations.
What should you bring to the appointment?
Bring a medication list, relevant diabetes-care information, and any retinal reports or treatment history. Ask the surgical team and prescribing clinicians who will give instructions for medicines around the procedure. Do not independently adjust diabetes treatment based on this article.
If your care is split between a Dallas retina office and a Plano surgery team, confirm how records and postoperative findings will be shared. Identify the clinician responsible for each part of the plan before choosing a date.
What should follow-up include?
Ask whether your retinal findings change the monitoring plan and which symptoms require an urgent call. Do not assume all postoperative blur is normal or wait until a distant routine appointment if vision suddenly worsens. Severe pain, a sudden change, or new flashes and floaters need prompt clinical advice.
For routine planning, a cataract consultation should produce a shared explanation of the lens problem, retinal findings, proposed sequence, and realistic goals. The goal is useful improvement with appropriate ongoing diabetic eye care, not a promise that one operation resolves every cause of blur.
Sources
Keep reading
Your exam can clarify which options fit your eyes. Visit our Plano team from anywhere in DFW.
Book a free visit